How the Anion Gap Assesses
The anion gap is a useful part of acid-base evaluation because it helps healthcare providers and students grasp how the major electrolytes interact to one another in the blood. It is not a literal measurement of a single substance. Instead, it is a calculated value derived from common serum chemistry tests that shows the relationship between measured cations and measured anions.
In clinical terms, the anion gap assists in identify whether a patient has an acid-base disorder, especially metabolic acidosis. When the body retains acids or reduces bicarbonate, the chemistry panel changes in expected ways. An elevated or unexpected gap can point toward hidden acids, also called unmeasured anions, that are not directly listed on a standard electrolyte panel.
The most important measured values in this calculation are sodium, chloride, and bicarbonate. Some formulas also include potassium, though many clinical settings omit it for simplicity. Because the result is derived from typical serum electrolytes and other blood chemistry data, the anion gap serves as a quick diagnostic tool during patient assessment.
An Anion Gap Calculator makes it more convenient to calculate anion gap values rapidly and consistently. That can support a more precise understanding of the cause of acidosis, whether the issue is a simple bicarbonate loss, an excess acid load, or another process affecting the body’s acid-base balance.
How to Work With the Anion Gap Calculator
To work with an Anion Gap Calculator, add the serum values for sodium, chloride, and bicarbonate from the lab test results. These values are usually measured in milliequivalents per liter, and the calculator applies the standard formula to calculate the result.
Most calculator tools are designed for quick bedside review or educational use. They assist convert a basic blood chemistry panel into a more meaningful metabolic acidosis evaluation. If you also have the albumin level available, a more advanced calculator may enable you to correct for albumin and produce a corrected anion gap.
Here is the usual process:
- Input the sodium value from the lab report. Enter chloride and bicarbonate values from the same sample if possible. As an option: input potassium if the calculator includes it. As an option: input albumin if you want a corrected value. Review the result against the expected reference range or normal range.
For precise interpretation, the numbers should come from the same blood draw whenever possible. Changes in timing, fluid status, or treatment can affect the result. The calculator is most useful when paired with the rest of the clinical picture rather than used as a standalone answer.
Anion Gap Equation and Computing Stages
The standard anion gap formula can be written as:
Na minus Cl minus HCO3
In expanded form, that means:
Anion gap = sodium - chloride - bicarbonate
Some clinicians include potassium in the calculation:
Anion gap = sodium + potassium - chloride - bicarbonate
This version may yield a somewhat higher result, but both approaches are used in practice. The key is to know which method the calculator is using so the interpretation matches the calculation.
To calculate the value stepwise:
- Begin with the sodium value. Subtract chloride. Take away bicarbonate. When potassium is included, enter potassium before subtracting chloride and bicarbonate.
Calculation example: If sodium is 140, chloride equals 102, and bicarbonate is 24, the calculation would be 140 - 102 - 24 = 14. If potassium is included at 4 as well, then 140 + 4 - 102 - 24 = 18.
This basic math can help identify an high anion gap, but interpretation depends on the lab’s procedures and the patient’s general condition. A result that seems abnormal should always be considered in the setting of symptoms, medications, and other lab results.
Expected Anion Gap versus High Anion Gap
A standard anion gap usually shows that the relationship between measured cations and anions is inside the expected reference range. That does not always mean the patient is normal, but it may imply that the acidosis, if present, is due to bicarbonate loss rather than https://anion-gap-help655.capitaljays.com/posts/anion-gap-calculator-for-uremic-acidosis increased presence of unmeasured acids.
A elevated anion gap is more concerning because it often points to the presence of extra acids in the bloodstream. This pattern is classically seen in high anion gap metabolic acidosis, where acids build up and bicarbonate drops as the body tries to counteract the acid load.
Grasping the difference is central to metabolic acidosis workup. A normal gap can be associated with intestinal losses, renal tubular issues, or bicarbonate loss. A high gap more often indicates hidden acid accumulation from conditions such as lactic acidosis, ketoacidosis, or kidney-related causes.
The anion gap is not a diagnosis by itself. It is a clue. The result should guide additional testing and support broader clinical reasoning rather than take the place of it.
Modified Anion Gap & Albumin Calculation
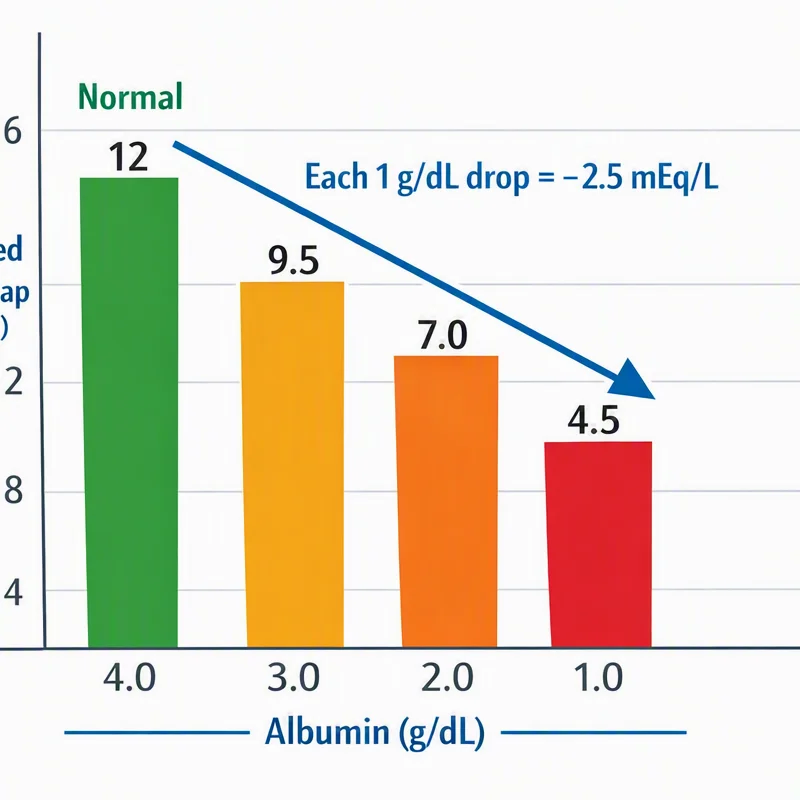
Albumin is a major unmeasured anion in blood, so decreased albumin can make the measured gap look lower than it really is. This is why many of the clinicians use a corrected anion gap when hypoalbuminemia is present.
If albumin is reduced, the usual gap may underestimate the severity of an acid-base problem. In that situation, the calculator may correct for albumin to more clearly reflect the underlying chemistry. This adjustment is especially important when interpreting lab results in severely ill patients or anyone with low protein levels.
Why does this matter? A patient can appear to have a normal anion gap even when excess acids are present if albumin is low enough. The corrected result can reveal a masked high anion gap that would otherwise be missed.
Albumin adjustment improves clinical interpretation because it accounts for one of the key contributors to the body’s electrical balance. In practice, corrected values are often more informative than the raw number alone, especially when evaluating potential acid-base disturbances.
Typical Causes of a Raised Anion Gap
An high anion gap typically suggests that the body has built up acids or other unmeasured charged substances. Several conditions are classically associated with this pattern, and identifying them helps narrow the cause of acidosis.
Lactic acidosis is a leading cause. It occurs when lactate builds up due to reduced oxygen supply, shock, severe illness, or other stressed conditions. Because lactate is an unmeasured anion, it increases the gap.
Acid buildup from ketones is another key cause. This may occur in diabetes, starvation, or alcohol-related states, where ketone bodies build up and shift the acid-base balance.
Uremia from reduced kidney function is also important. In severe renal failure, acids are not cleared effectively, and retained toxins lead to a higher gap.
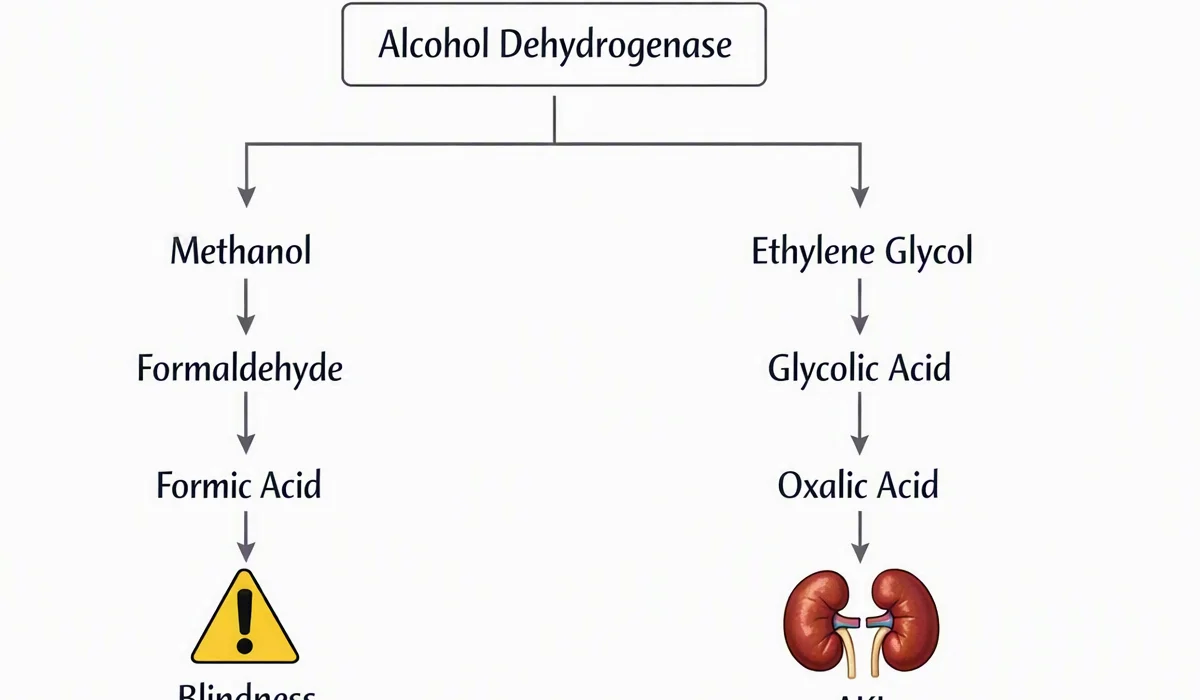
Other causes can include toxins, medications, and metabolic conditions that promote acid formation or reduce acid removal. The main point is that a high gap should prompt a search for occult acid production or poor clearance rather than a narrow focus on the number itself.
How to Understand Results in Medical Context
Reading the anion gap correctly requires more than just a number. A good clinical interpretation blends the gap with signs, vital signs, history, medications, and other lab values such as an arterial blood gas.
The arterial blood gas helps show whether the patient actually has acidemia or high pH, whether compensation is occurring, and whether the primary disorder aligns with the chemistry panel. The anion gap then adds another layer by identifying whether the metabolic problem is likely due to added acids or bicarbonate loss.
The delta gap is also valuable in more complex cases. It contrasts the change in the anion gap with the change in bicarbonate to look for mixed disorders. For example, a patient may have high gap metabolic acidosis along with a separate metabolic alkalosis or a concurrent normal gap acidosis.
This is why the Anion Gap Calculator is best viewed as part of a broader workflow. It aids decision-making, but the final interpretation should combine the complete acid-base picture, including the patient’s clinical status and any possible base deficit.
Limitations of Anion Gap Calculation
Although the anion gap is helpful, it has several limitations. One issue is lab variation. Different instruments, assay methods, and reporting practices can produce slightly different results, which means the reference range may differ by laboratory.
Another limitation is that the gap only shows measured and unmeasured anions indirectly. It does not identify the specific acid responsible. A high value may suggest a disorder, but it cannot distinguish between lactic acidosis, ketoacidosis, or other causes without additional context.
Electrolyte measurement problems can also affect accuracy. Severe electrolyte disorders, changes in protein concentration, or unusual blood chemistry patterns may distort the result. In addition, the presence of certain ions can change how the gap appears even if the true acid burden has not changed dramatically.
Due to these constraints, the anion gap should be used as a component of a complete acid-base disorder review. It serves as a valuable indicator, but not a final answer. The most effective use of the calculator is to aid thoughtful interpretation of lab results, not to substitute for clinical reasoning.
FAQ About the Anion Gap Calculator
What is an anion gap calculator used for?
An Anion Gap Calculator is used to determine anion gap values from routine lab results and assist with acid-base evaluation. It is especially useful in metabolic acidosis evaluation because it can reveal whether the problem is related to hidden acids, bicarbonate loss, or another acid-base disorder.
What is the normal anion gap range?
The reference range for the normal anion gap differs by laboratory and by whether potassium is included in the formula. In general, many labs consider a value in the low to mid-teens to be normal, but the exact range should always be interpreted using the reporting lab’s stated normal range.
How do you calculate the anion gap from lab values?
Use the standard anion gap formula: sodium - chloride - bicarbonate. Some versions include potassium before subtracting chloride and bicarbonate. The calculator performs this step directly using the provided serum electrolytes, making it easier to assess blood chemistry results quickly.
Why do you correct the anion gap for albumin?
You correct for albumin because low albumin can mask a true gap elevation. In hypoalbuminemia, the measured value may look normal even when unmeasured acids are present. A corrected anion gap gives a more reliable picture of the patient’s acid-base status.
What conditions cause a high anion gap?
Common causes of a high anion gap include lactic acidosis, ketoacidosis, and uremia. Severe renal failure, toxins, and other causes of retained acids can also lead to an elevated value. The result should always be interpreted in the context of the full clinical picture and any associated arterial blood gas findings.