What Does the Anion Gap Mean?
The anion gap is a computed value helping evaluate plasma and serum electrolytes in a standard electrolyte panel. It reflects the gap between the major measured cations and anions, mainly sodium on one side and chloride plus bicarbonate on the other. Because routine lab testing does not measure every charged particle in blood chemistry, the anion gap approximates the amount of unmeasured anions and helps assess acid-base balance.
This concept is rooted in electroneutrality, the principle that plasma must remain electrically balanced overall. The calculated anion difference is not a direct measurement of a single substance; instead, it is a practical guide in clinical interpretation and diagnostic evaluation. When the gap is abnormal, it can suggest a metabolic disturbance even before the underlying cause is fully known.
The anion gap calculator is designed to simplify this process. By entering common lab values, you can determine whether the result falls within the expected lab reference range and decide whether further testing or closer review is needed. In practice, the anion gap is often used as part of a wider electrolyte panel and overall assessment of serum chemistry.
How the Anion Gap Calculator Works
An anion gap calculator relies on a basic formula based on the observed concentrations of chloride and bicarbonate compared with sodium. The usual formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)This equation helps identify whether the body is building up extra acids or depleting key buffering capacity. The calculation is rapid, but the meaning depends on the full clinical context. A normal number does not always rule out illness, and an abnormal number does not automatically confirm one diagnosis.
The calculator is particularly useful because it converts a set of routine lab values into a result that supports result interpretation. If the numbers are outside the expected reference interval, clinicians may consider whether there are additional acids, changes in protein balance, or even a lab measurement issue. In other words, the calculator does more than offer a number; it supports risk stratification during evaluation of possible acid-base problems.
How to Find Anion Gap Step by Step
To carry out the calculation, begin with the values from a standard chemistry panel. Rely on serum sodium, serum chloride, and serum bicarbonate from the same sample whenever possible. Consistency is important because small differences in sampling or timing can affect the result.
Use these steps:
- Identify the sodium value from the lab report. Add the chloride and bicarbonate values together. Remove that sum from the sodium value.
For instance, if serum sodium is 140, serum chloride is 104, and serum bicarbonate is 24, the anion gap is 140 − (104 + 24) = 12. This result may fall within a typical normal range, depending on the lab method and local reference interval.
As this is based on routine serum chemistry, it is important to check the numbers carefully. A small transcription mistake can modify the answer significantly. The calculator is a practical tool, but accurate input is essential for reliable diagnostic evaluation.
Standard Anion Gap Range and Reference Limits
The expected range for anion gap differs by laboratory because different analyzers and methods produce slightly different results. For this reason the normal range on the report should always be checked in place of relying on a one universal cutoff. In many settings, the reported test values fall into a narrow band, but the exact range depends on the assay and whether potassium is included in the calculation.
Albumin also affects the expected result because it is one of the main unmeasured anions in plasma. When albumin is low, the anion gap may appear incorrectly normal or low even if clinically important acids are present. For that reason, understanding the local test reference range and considering adjustment for albumin are both essential.
A result should always be interpreted together with symptoms and other chemistry findings. A single number cannot replace the broader picture of blood chemistry, especially when assessing possible acid-base abnormalities.
Increased anion gap Causes
A elevated anion gap often suggests additional unmeasured acids in the bloodstream and is commonly associated with acidic blood imbalance. The most common form is increased anion gap metabolic acidosis, which often indicates that acid production has risen, acid clearance has decreased, or each.
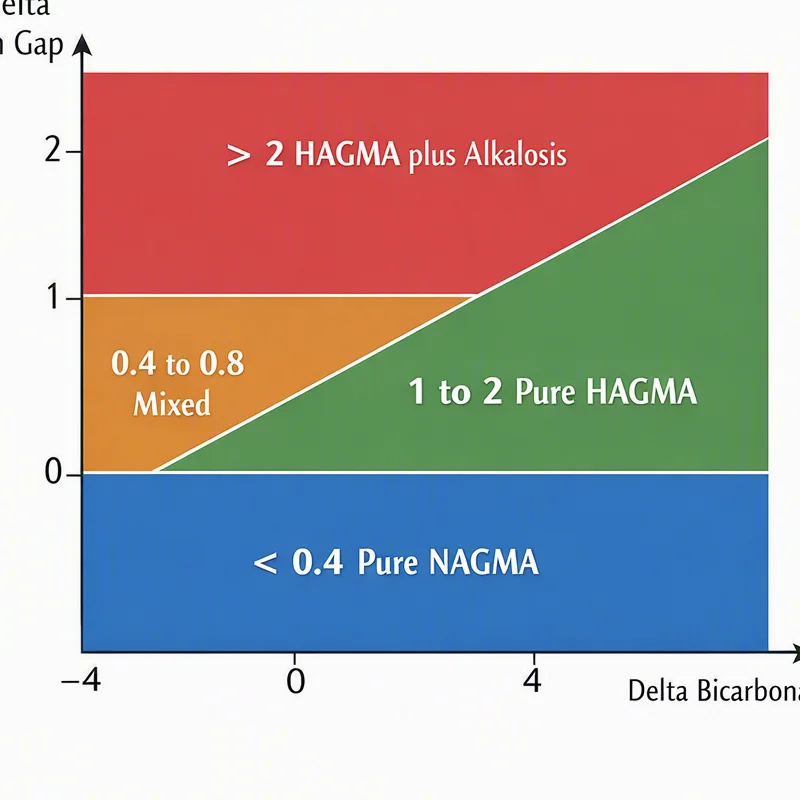
Common causes include:
- Excess lactic acid, frequently related to tissue hypoperfusion, severe infection, or other systemic stress. Acid buildup from ketones, such as diabetic ketoacidosis or starvation ketosis, where ketone acids collect. Impaired kidney function, in which the kidneys cannot remove acids properly. Poisonous alcohols, including substances that can generate acidic metabolites.
Other toxins may also be involved, and the pattern can help guide urgent clinical assessment. A high value is not a diagnosis by itself; it is a signal to investigate the cause of the acid-base abnormality. In practice, the calculator supports early recognition of an abnormal pattern so clinicians can focus on confirmatory tests, evaluate symptoms, and assess severity.
Because many causes overlap, the anion gap should be interpreted alongside patient history, clinical exam results, and other lab data. The presence of vomiting, altered breathing, dehydration, or confusion can alter the differential and point toward a specific metabolic disturbance.
Decreased Anion Gap Factors
A decreased anion gap is less common, but it can still be medically significant. One of the most important causes is low albumin, since albumin is a major contributor to the usual charge balance. When albumin falls, the measured gap may also decrease, even if there is no large alteration in the actual acid-base state.
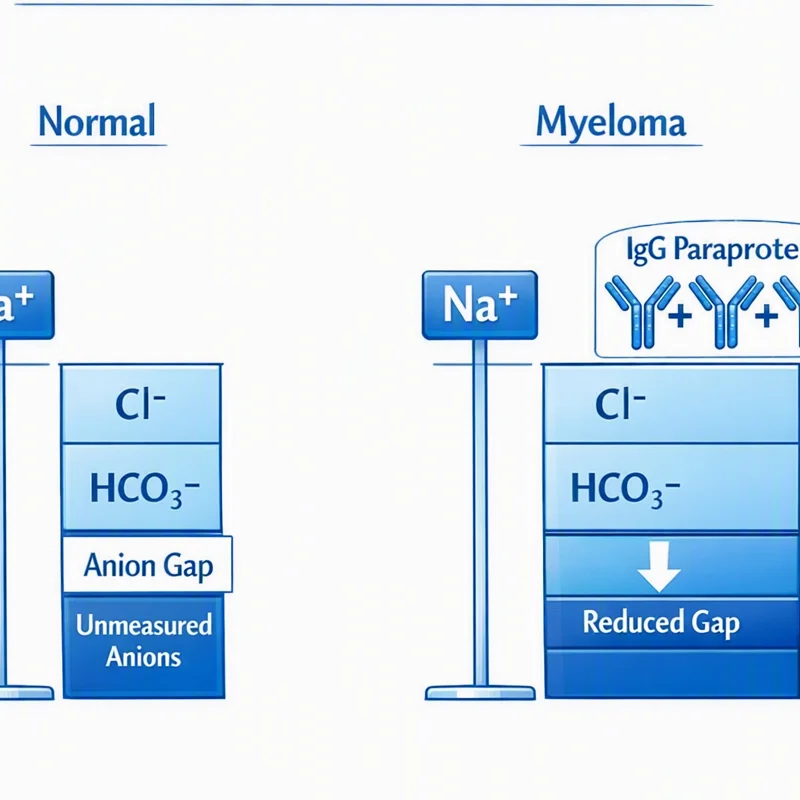
Other causes include myeloma, where abnormal proteins can alter the charge balance in blood. Hypercalcemia may also be associated with a reduced value in some cases. Sometimes the issue is not a medical condition at all but laboratory error or a pre-analytic problem such as sample contamination or instrument variation.
Because a decreased reading may reflect either real pathology or analytical error, it should not be ignored. If the result is unexpected, clinicians often repeat the test, review the full electrolyte profile, and consider whether the finding matches the patient’s symptoms and other blood chemistry values. This is where the calculator is useful as a screening and interpretation aid, but not as a final answer.
How Serum Albumin Influences the Anion Gap
Correction for albumin is important because albumin is a principal negatively charged protein in the plasma and contributes to overall electrical balance. Since albumin behaves as an unmeasured anion, low albumin can reduce the apparent anion gap. In patients with significant hypoalbuminemia, the uncorrected number may fall short of the real amount of acid accumulation.
The corrected anion gap helps compensate for this by modifying the measured value based on the serum albumin concentration. Various institutions may use slightly different adjustment formula approaches, but the overall goal is the same: to determine what the gap would be if albumin were normal. This enhances interpretation when evaluating possible unmeasured anions in acid-base problems.
Albumin correction is especially useful when clinical suspicion is high but the measured gap looks normal. In that setting, the correction can reveal hidden metabolic acidosis and raise the quality of diagnostic evaluation. It also helps reduce false reassurance when low albumin is masking the true picture.
Medical Assessment of Results
The anion gap is most useful when interpreted as part of a full acid-base disorder assessment. A number deviating from the normal range may indicate an electrolyte imbalance, but the significance depends on the patient’s complaints, https://privatebin.net/?8e4fcf40c884b9c3#4MjJsSMK5D8ent9SYvj9suh2QWPH27ckiBYof1bSESXN vital signs, and other labs. For example, a high gap with low bicarbonate is consistent with an acid load problem, while a low or normal gap does not exclude disease if albumin is reduced.
An arterial blood gas can help determine whether the patient truly has acidemia or alkalemia and whether respiratory compensation is appropriate. Pairing the anion gap with blood gas data improves clinical interpretation and supports more accurate symptom assessment. This is especially valuable when the presentation is complicated.
In practice, the anion gap is one piece of the overall puzzle. It can help refine the differential, but final interpretation requires the full clinical context, including medications, kidney function, perfusion status, nutritional state, and possible exposures. That broader view helps differentiate a transient metabolic disturbance from a more serious condition.
Frequent Use Cases for the Anion Gap Calculator
The anion gap calculator is used often in emergency medicine and the ICU, where rapid decision-making is crucial. In those settings, clinicians often need a quick way to spot patients with possible acid accumulation, especially when blood gas or chemistry results are being reviewed in real time.
It also serves as a helpful screening and diagnostic tool in outpatient and inpatient care. When a routine electrolyte panel shows an unexpected change, the calculator helps determine whether the pattern suggests a more serious acid-base issue or a less urgent explanation. This can direct next steps in evaluation and help prioritize confirmatory workup.
Since it is simple to use, the calculator enables rapid risk stratification. It does not replace formal medical evaluation, but it does help clinicians identify which patients may need additional labs, closer observation, or urgent treatment.
Limitations and When to Confirm with Lab Testing
While useful, the calculator has limitations. The result depends on accurate inputs and on the reliability of the underlying lab measurement. Even minor measurement error can alter the final number, particularly when the gap is near the cutoff between normal and abnormal.
A venous blood test is often the source of the electrolyte values used in calculation, and repeat sampling may be needed if the result does not fit the clinical picture. Repeat testing is especially important when the finding is unexpected or when a treatment decision depends on it. The overall precision of the result improves when the sample is collected correctly and analyzed promptly.
Follow-up testing is also important when albumin is very low, when there is concern for toxic ingestion, or when the patient has a complex metabolic disturbance. In those cases, the calculator should be considered a piece of broader clinical interpretation, not the final word.

FAQ
What is a normal anion gap?
A normal anion gap is the result expected within a laboratory’s reference range, but the exact cutoff depends on the method used and the local lab reference range. Because analyzers differ, it is best to compare the result with the specific report rather than a universal number. Albumin level can also change the expected value.
How do I calculate the anion gap from sodium, chloride, and bicarbonate?
Follow the standard formula: sodium minus the sum of chloride and bicarbonate. In other words, sodium − ( chloride + bicarbonate). This is the main calculation used by any anion gap calculator. Make sure the values come from the same blood sample to improve accuracy.
Why should I correct the anion gap for albumin?
Correcting for albumin matters because albumin is a key unmeasured anion and influences overall ionic balance. With low albumin, the measured gap may appear incorrectly normal or low. The corrected anion gap offers a more accurate estimate of the true metabolic picture.
What leads to a high anion gap?
A high anion gap is often caused by metabolic acidosis from extra acids in the blood. Common causes include lactate buildup, ketone buildup, kidney dysfunction, and exposure to toxic alcohols. Other poisons may also play a role, so the result should be interpreted with the full clinical context.
Can a low anion gap be a sign of a medical problem?
It can. A low anion gap can reflect low albumin, multiple myeloma, or high calcium, and it can also result from laboratory error. If the value is unexpected, it should be reviewed carefully and often confirmed with repeat testing. The finding is not necessarily dangerous, but it should not be dismissed without further evaluation.