An anion gap calculator is a practical diagnostic tool for assessing an acid-base disorder in young patients. It helps clinicians interpret an electrolyte imbalance, determine the likely cause of metabolic acidosis, and determine what additional testing may be needed. As pediatric patients have different physiology, growth patterns, and common illness patterns than adults, the clinical interpretation of the anion gap requires careful attention to age, albumin, and the overall picture of lab values and symptoms.
When used correctly, this simple calculation can reveal clues about unmeasured anions in the blood and support a broader metabolic evaluation. It is not a stand-alone diagnosis. Instead, it is part of a larger review of serum chemistry, the child’s condition, and any signs of an acidic state that may need urgent care.
How the Anion Gap Measures in Children
The anion gap is a calculated value that approximates the disparity between recorded positively charged and negatively charged particles in the blood. In practice, it is derived from serum sodium, serum chloride, and serum bicarbonate. This calculation formula is a way to detect an anion difference that may indicate extra acids or other unmeasured anions.
In children, the anion gap is especially valuable when evaluating metabolic acidosis. If the gap is elevated, it often indicates the body has accumulated acids that are not directly measured on a basic electrolyte panel. If the gap is normal, the problem may be related to loss of bicarbonate or another process that does not increase unmeasured acids.
Grasping the buffer system matters here. The body maintains pH through coordinated changes in respiration, kidney function, and bicarbonate balance. When that system is disrupted, the anion gap can provide useful interpretive guidance about the direction of the problem. Still, the number itself must be viewed in context with the child’s symptoms, hydration status, and other blood chemistry findings.
Using an Anion Gap Calculator
An anion gap calculator usually requires three inputs: sodium value, serum chloride, and serum bicarbonate. These numbers come from a standard electrolyte panel or broader serum chemistry testing. The calculator then follows the standard formula to calculate the anion gap.
The usual formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Some laboratories use variations that account for potassium, but the sodium-based formula is widely used for pediatric assessment because it is straightforward and uniform. The result should then be compared with the lab’s reference interval and the child’s clinical status.
To use the calculator effectively:
- Provide the most recent blood chemistry values from the same sample when possible. Look for obvious data entry errors before relying on the result. Review whether the child has signs of dehydration, infection, or another condition that changes acid-base balance. Evaluate the number alongside the bicarbonate level, not in isolation.
The calculator is best thought of as a rapid screen for an acid-base disorder. It does not substitute for clinical reasoning or a full differential diagnosis. In pediatric care, the real value is in linking the calculation to the child’s symptoms, exam findings, and other lab values.
Children's Reference Values and Standard Values
A pediatric reference range for the anion gap may differ slightly by laboratory, developmental stage, and testing method. A anion gap within normal range does not mean the child is healthy, and an abnormal value does not always mean a medical problem. It simply provides a clue that must be interpreted carefully.
Young patients may have developmental differences in serum chemistry because renal function, overall body water, diet, and illness patterns shift during development. Babies, children, and adolescents may all show small https://anion-gap-estimator489.quantlynix.com/posts/how-alcoholic-ketoacidosis-affects-the-anion-gap differences in electrolytes and acid-base balance. For this reason, laboratory-specific norms are important.
Laboratory variation also matters. Different analyzers and measurement methods can change the reported result. A number that appears mildly elevated in one lab may be considered normal in another. That is why pediatric interpretation should always use the site-specific reference range and not rely on a single universal cutoff.
In general, the anion gap is used as a screening tool rather than a conclusive test. A mildly different value may reflect typical variation, while a larger abnormality suggests a more notable acid-base problem that should be evaluated further.
Accounting for the Anion Gap for Serum Albumin
Serum albumin serves as a major unmeasured negatively charged ion in blood. If albumin levels are low, the measured anion gap may seem falsely normal or only mildly elevated even when an acid load is present. That is why albumin correction is so important in pediatric care.
Hypoalbuminemia can occur with illness, inflammation, poor nutrition, kidney disease, or fluid shifts. In such cases, the uncorrected number may underestimate the severity of the problem. Calculating a corrected anion gap offers a better estimate of the true acid burden and improves the accuracy of the clinical interpretation.
While formulas may vary, the principle is consistent: if albumin is low, the gap should be adjusted upward to account for the missing negative charge. This is commonly referred to as the albumin-adjusted gap. The correction is especially important when evaluating a child with a suspected acid-base disorder but a less dramatic anion gap than expected.
Using the corrected result promotes better diagnostic reasoning. It can help distinguish a truly normal gap from one that only appears normal because of low albumin. In a child with metabolic acidosis, that distinction can change the differential diagnosis and the next steps in care.
Increased metabolic acidosis with a high anion gap in Pediatrics
High anion gap metabolic acidosis means there is a accumulation of acids or substances that form acid that are not directly measured in the standard electrolyte panel. This is one of the main reasons clinicians use the anion gap calculator in pediatrics. It narrows the differential diagnosis and aids in identifying potentially urgent conditions.
Common causes in children include lactic acidosis, ketoacidosis, and kidney failure. These conditions raise unmeasured acids in the blood, reducing bicarbonate and increasing the gap. In children, lactic acidosis may occur with inadequate perfusion, major infection, or shock. Ketoacidosis can occur with diabetes, prolonged fasting, or other states of insufficient carbohydrate intake. Renal failure impairs the body’s ability to excrete acid, resulting in accumulation.
Other less common causes also belong in the differential diagnosis, especially if the presentation is critical or unexpected. A child with an elevated gap may need urgent evaluation for toxin exposure, tissue hypoxia, or inherited metabolic disorders depending on the history and exam.
When the gap is high, the next question is not just “How high is it?” but “Why is it high?” This question guides further testing, treatment priorities, and the level of monitoring needed.
Standard Anion Gap Metabolic Acidosis in Pediatrics
Normal-gap metabolic acidosis is sometimes called chloride-responsive acidosis because chloride commonly increases as bicarbonate falls. The anion gap stays within the expected interval, but the child still has acid-base acidosis. This is why a normal result should not be dismissed if the clinical picture suggests an acid-base problem.
Two common pediatric causes are loose stools and renal tubular acidosis. With diarrhea, the body loses bicarbonate through the gastrointestinal tract, leading to base loss. In renal tubular acidosis, the kidneys fail to appropriately reclaim bicarbonate or excrete acid, so acid builds up without a large increase in unmeasured anions.
Because the anion gap stays normal, recognition depends on combining the calculation with the bicarbonate level and the overall clinical picture. A child with ongoing diarrhea, poor intake, or growth concerns may have a normal-gap acidosis that is simple to overlook without careful review of the electrolyte panel.
This is where pediatric assessment matters. A normal gap is not reassuring if the child appears unwell, dehydrated, or acidotic. It simply points clinicians toward a different mechanism of acid-base disruption.
Common Reasons, Key Signs, and Subsequent Actions
Several common pediatric disorders can alter the anion gap and should be considered during interpretation. Harmful swallowing is one important cause of high-gap acidosis, especially when the history is unclear or the child has sudden neurologic changes. Sepsis can lead to lactic acidosis through poor tissue perfusion and systemic inflammation. Dehydration may alter labs and worsen acid-base imbalance, especially when accompanied by vomiting, diarrhea, or poor intake.
An arterial blood gas can be extremely helpful when the electrolyte panel suggests a problem but the severity is uncertain. It provides a direct look at pH, carbon dioxide, and bicarbonate status, helping confirm whether the child truly has metabolic acidosis and whether respiratory compensation is present.
Further steps depend on the clinical setting. In a stable child, repeat testing and careful history may be enough. In a child who appears toxic, lethargic, or severely dehydrated, urgent evaluation is needed. Additional studies may include glucose, lactate, ketones, kidney function tests, toxicology testing, and infection workup. The anion gap is best used as part of a broader metabolic evaluation rather than as a stand-alone answer.
Constraints of Anion Gap Calculation in Children
Although useful, the anion gap has important limitations in pediatric interpretation. One major issue is combined acid-base disturbances. A child may have more than one process at the same time, such as vomiting plus sepsis, which can make the gap harder to interpret. In such cases, a “normal” value may hide a significant disturbance, or a high value may reflect combined processes rather than a single cause.
Testing error is another concern. Pre-analytic issues, sample handling problems, or transcription mistakes can distort serum sodium, serum chloride, or serum bicarbonate values. Even small errors can shift the calculated result enough to mislead clinical reasoning.
The albumin effect is especially important in children with sickness, inflammation, or inadequate intake. If serum albumin is low, the uncorrected number may mask the real acid burden. That is why a adjusted result can be more useful than the raw value alone.
Finally, pediatric interpretation requires context. Growth stage, illness severity, hydration, kidney function, and medication exposure all influence blood chemistry. A value should not be interpreted in isolation from the child’s symptoms, exam, and additional testing.
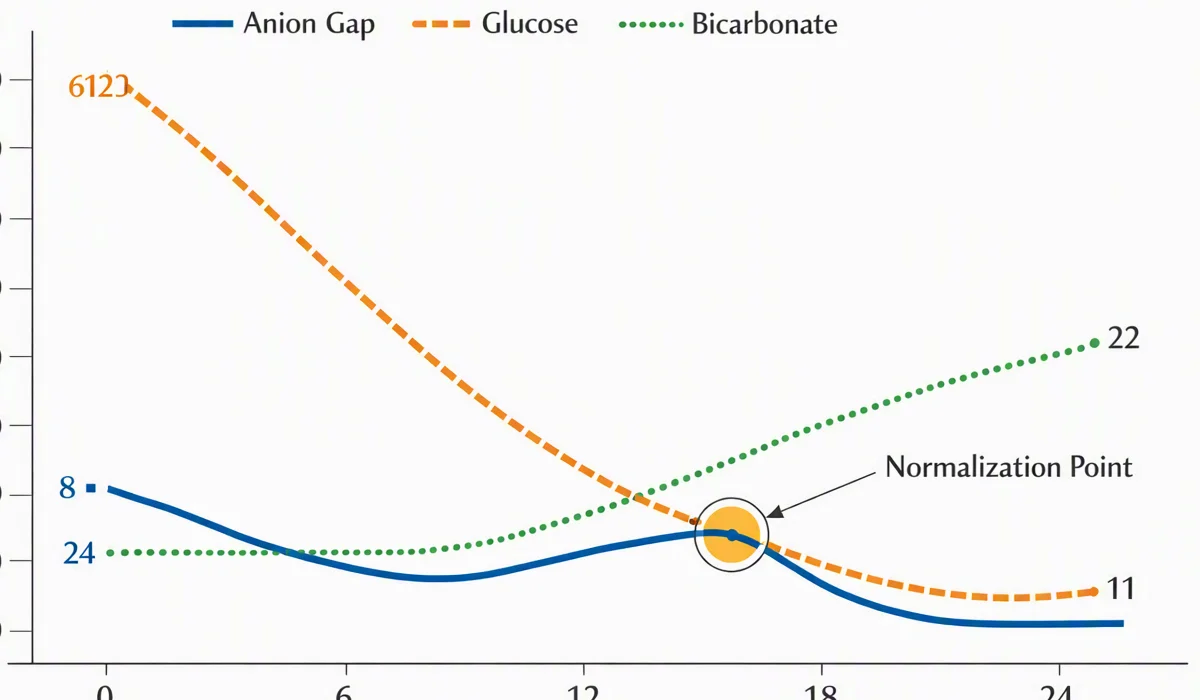
Used wisely, the anion gap calculator supports strong diagnostic reasoning. Used alone, it can create error. The best approach is to consider the calculation as one part of a carefully integrated clinical picture.

Frequently Asked Questions
What is the normal anion gap in pediatric patients?
The pediatric reference range for the anion gap depends on the laboratory method and the child’s age, so there is no single universal number. In general, clinicians check the result with the lab’s stated normal range and consider whether serum albumin is low, because hypoalbuminemia can make the gap look smaller than expected.

How do you calculate the anion gap in children?
The standard anion gap calculation uses serum sodium minus the sum of serum chloride and serum bicarbonate. This calculation formula is commonly built into an anion gap calculator and is usually applied to values from the same electrolyte panel for proper clinical interpretation.
Why should albumin be considered when interpreting the anion gap?
Serum albumin is a major unmeasured anion, so low albumin can obscure an elevation in the gap. Using an albumin correction helps determine the corrected anion gap and reduces the risk of missing an acid-base disorder in a child with hypoalbuminemia.
What is behind a raised anion gap metabolic acidosis in pediatrics?
Frequent sources of high anion gap metabolic acidosis in children include lactic acidosis, ketoacidosis, and renal failure. Additional key possibilities include toxic ingestion, sepsis, and additional disorders that elevate unmeasured acids in the blood.
Can metabolic acidosis occur with a normal anion gap?
Yes. A child can have normal anion gap metabolic acidosis when bicarbonate is lost or acid handling is impaired without accumulation of unmeasured anions. Typical examples include diarrhea and renal tubular acidosis, both of which can cause bicarbonate loss and true metabolic acidosis despite a normal gap.