An Anion Gap Calculator is a practical tool for determining the anion gap from standard blood chemistry findings. By using sodium, chloride, and bicarbonate values, it helps clinicians and students quickly assess acid-base balance and spot patterns that may indicate an underlying disorder. Because these numbers are already part of a routine serum chemistry panel, the calculation can be performed promptly as a diagnostic aid during everyday interpretation of an electrolyte panel.
This section centers on calculator use with chloride values and bicarbonate values, how the anion gap calculation functions, and how to read the result in real-world clinical context. It also covers formula variations, including potassium and albumin adjustments, so you can better understand the corrected anion gap when needed.
Understanding the Anion Gap?
The anion gap is a computed number that shows the gap between measured cations and measured negatively charged ions in the blood. It is a method to evaluate whether there may be excess unmeasured anions affecting the body’s acid-base balance. In daily practice, the calculation is obtained from serum electrolytes reported on a serum chemistry panel or more comprehensive blood chemistry test.
Although the anion gap is not a direct measurement of a single substance, it is useful because shifts in the number can point toward an acid-base disorder or another form of metabolic derangement. A within-range result does not exclude disease, but an abnormal result can support further evaluation and help identify the underlying cause.
In practical terms, the anion gap is often used as a screening tool when reviewing electrolyte patterns. It is especially important helpful when a patient has signs of metabolic acidosis, since the result can show whether the condition involves higher acids, loss of bicarbonate, or another imbalance in the body’s buffer system.
How an Anion Gap Calculator Works
An Anion Gap Calculator applies a simple formula based on common laboratory measurements. The calculator typically asks for sodium, chloride, and bicarbonate values, then calculates the anion gap formula on its own. This makes it easier to get a quick result without doing the math by hand.
The classic version of the calculation is:
Anion gap = sodium - chloride - bicarbonate
Some calculators display the result using the same structure as Na minus Cl minus HCO3. In that format, sodium is the main measured cation, while chloride and bicarbonate are the main measured anions. The difference between them approximates the amount of unmeasured anions in the blood.
For a user, the workflow is straightforward:
- Enter the sodium value from the lab report. Input the chloride value. Input the bicarbonate value, often listed as CO2 or HCO3. Examine the calculated anion gap and review it with the lab’s reference range.
This approach is especially valuable when reviewing routine serum electrolytes and trying to determine whether an electrolyte imbalance may be altering the overall pattern.
Anion Gap Formula and Typical Variations
The most familiar formula is Na minus Cl minus HCO3, but there are regular variations depending on the lab and clinical setting. Some clinicians include potassium in the formula, which alters the result a bit. Others rely on the sodium-based calculation because potassium plays a smaller role to the routine interpretation in many settings.
One reason for variation is that the anion gap is influenced by factors such as albumin, a major unmeasured negatively charged protein. When albumin is low, the measured gap may appear reduced than expected. In those cases, a corrected anion gap may offer a more accurate estimate of the patient’s true status.
Albumin correction matters because albumin is one of the largest contributors to the normal gap. If albumin drops, the calculated number can downplay the burden of unmeasured anions. A corrected value can therefore enhance the clinical picture, especially when evaluating a suspected acid-base disorder.
Key considerations to keep in mind:
- The calculator may rely on sodium, chloride, and bicarbonate only. Some formulas incorporate potassium, which can a little raise the gap. Albumin adjustment may be needed when protein levels are off. Always review the result with the relevant laboratory reference interval.
Because formulas differ, the same patient may have different results depending on the method used. That is why understanding the specific anion gap formula built into the calculator is essential for accurate interpretation.
Understanding the Calculation
Understanding the result usually starts with the lab’s reference range. Results are often classified as normal anion gap, high anion gap, or low anion gap. The exact measured range varies by laboratory and by whether potassium is included, so the calculator should always be interpreted alongside the reported local range.
A typical anion gap suggests that the distribution of measured ions is within expected limits. Still, a normal finding does not rule out disease, particularly if other findings point to a meaningful disturbance in acid-base balance. For example, a patient may still have metabolic disturbances that are better understood through the bicarbonate level, chloride level, and overall patient picture.
A elevated anion gap typically indicates increased acids or build-up of unmeasured substances. In contrast, a decreased anion gap is less common and may reflect low albumin, measurement errors, or particular conditions that alter the electrolyte pattern.
When interpreting interpretation, it helps to ask:
- Is the result within the stated reference range? Are the chloride and bicarbonate values consistent with the gap? Does the patient have signs of metabolic acidosis or another metabolic derangement? Could albumin be altering the apparent result?
Because the anion gap is a diagnostic aid, not a final diagnosis, interpretation should always be integrated with the rest of the lab data and the patient’s symptoms.
Reasons of a High Anion Gap
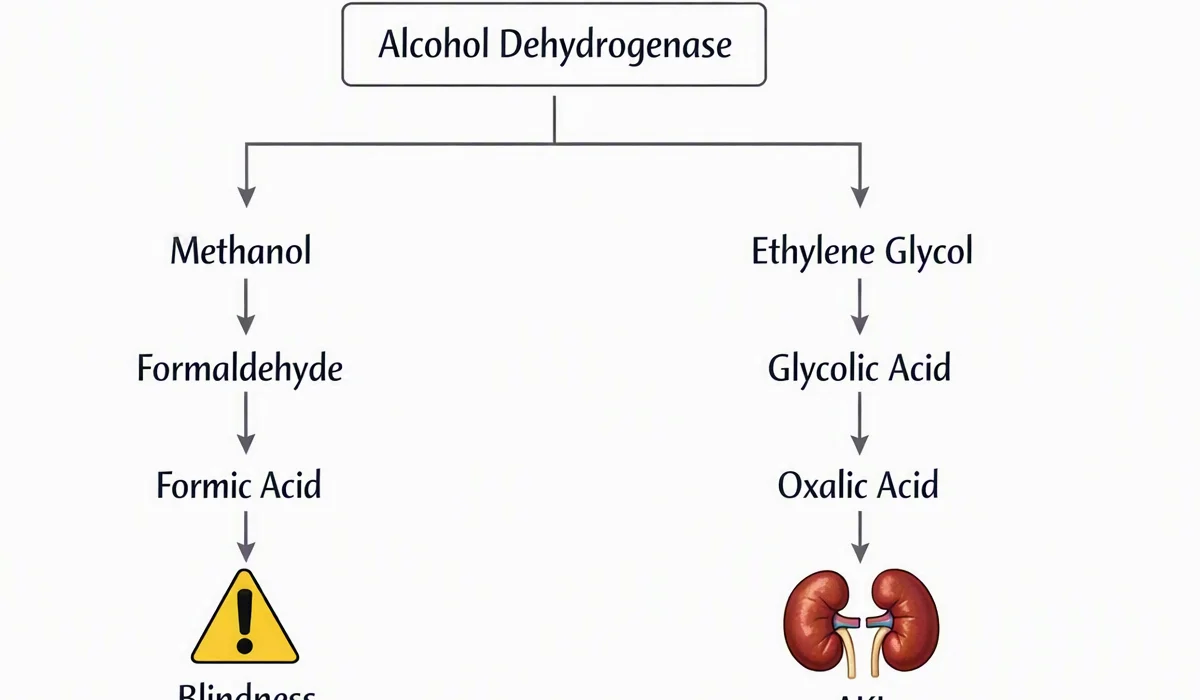
A high anion gap often indicates accumulation of acids or other nonmeasured substances in the blood. Among the most important causes are lactic acidosis, ketoacidosis, renal failure, and contact to toxic alcohols. These conditions can all produce a substantial acid load or limit the body’s ability to remove acids efficiently.
Lactic acidosis occurs when lactate accumulates, often in settings of inadequate tissue oxygen delivery, severe illness, or other physiologic stress. Ketoacidosis may occur when ketone production increases, such as in uncontrolled diabetes, prolonged fasting, or alcohol-related metabolic changes. Renal failure can reduce acid https://anion-gap-estimator556.huicopper.com/anion-gap-calculator-online-for-fast-serum-analysis excretion, allowing acids to accumulate. Toxic alcohols are a classic trigger of a high gap and should be considered when the history or presentation suggests ingestion.
These causes are often evaluated together with the patient’s bicarbonate level, since a low bicarbonate value frequently accompanies high-gap metabolic acidosis. However, the exact pattern can vary, which is why the Anion Gap Calculator is best used as part of a broader workup rather than in isolation.
Reasons of a Low Anion Gap
A decreased anion gap is less common but still clinically meaningful. One of the most important causes is hypoalbuminemia, because albumin is a major unmeasured anion. If albumin drops, the calculated gap may decrease even if no other major disorder is present.
Another frequent cause is lab error. Since the anion gap depends on sodium, chloride, and bicarbonate, even small measurement problems can affect the result. A repeat test may be appropriate if the finding does not fit the clinical picture.
Other possible causes include hypercalcemia and multiple myeloma. In some cases, abnormal proteins or changes in other measured ions alter the balance enough to lower the gap. When the result is unexpectedly low, checking albumin and considering a corrected anion gap can be particularly helpful.
In short, a low result should not be dismissed. It may reflect a real underlying problem, or it may be a clue that the calculator output needs to be rechecked against the actual laboratory values and the broader clinical context.
Why Chloride and Bicarbonate Are Important
The chloride concentration and bicarbonate level are key to the calculation because they are the principal measured anion inputs used in most versions of the formula. If chloride rises or bicarbonate falls, the gap can change suddenly, which makes these numbers very useful in evaluating electrolyte disturbance and acidic metabolic state.
Chloride often increases in conditions where bicarbonate is lost or diluted, while bicarbonate commonly decreases in acidotic states. The relationship between the two provides insight into how the body is handling acids and bases. This is why anion gap review is frequently part of the broader assessment of acid-base balance.
Using chloride and bicarbonate values together can reveal patterns that might not be obvious from either number alone. For example, a low bicarbonate with a normal or elevated chloride may point to a different process than a low bicarbonate with a high gap. This makes the anion gap a effective way to structure the interpretation of serum electrolytes.
Step-by-Step Sample Calculation
Here is a straightforward example using typical sample values to show the hand calculation process.
- Sodium = 140 Chloride = 104 Bicarbonate = 24
Using the anion gap formula:
Anion gap = sodium - chloride - bicarbonate
Insert the values:
140 - 104 - 24 = 12
The calculated anion gap in this example is 12. If the laboratory’s reference range includes 12, then this would be interpreted as a normal anion gap. If the lab’s range differs, the interpretation should follow the local laboratory reference.
Then consider a second example:
- Sodium = 138 Chloride = 100 Bicarbonate = 16
Calculation:
138 - 100 - 16 = 22
This greater result can suggest a high anion gap, which would prompt review for causes such as lactic acidosis, ketotic acidosis, renal failure, or toxic alcohol ingestion. The ultimate interpretation depends on symptoms, history, and the rest of the blood chemistry.
Limitations and Clinical Considerations
Even a properly designed Anion Gap Calculator has its limits. One major issue is albumin correction. Because albumin affects the gap, a patient with low albumin may have a falsely low or normal result unless a adjusted anion gap is considered.
Laboratory variability is another key factor. Different analyzers and local methods can lead to slightly different sodium, chloride, and bicarbonate results. So the calculator output may shift depending on where the sample was processed. For that reason, comparison with the relevant expected range is essential.
Interpretation in context also matters. A numerical result should be read in light of symptoms, medication use, recent illness, and the larger pattern of serum electrolytes. Sometimes an arterial blood gas test is needed to better define the acid-base status, especially when the bicarbonate level and clinical presentation do not match the calculated gap.
To put it another way, the calculator is useful, but it is not a substitute for professional evaluation. It works best as part of a complete assessment of the overall clinical picture, especially when the result could signal a serious disorder or a rapidly changing condition.
Frequently Asked Questions
How do you calculate the anion gap using chloride and bicarbonate values?
Use the usual formula for anion gap: sodium minus chloride minus bicarbonate, often written as Na - Cl - HCO3. Enter the sodium, Cl, and bicarbonate values into an Anion Gap Calculator, or calculate it manually by subtracting chloride and bicarbonate from sodium. Some formulas also include potassium, so check which version is being used.
What is a normal anion gap range?
A normal anion gap varies with the laboratory and the equation used, so the best reference is the site-specific reference range. Many labs provide a range that is based on their analyzer and whether potassium is included. Always evaluate the number using the lab’s own laboratory reference interval rather than assuming one universal value.
What does a high anion gap mean?
A high anion gap often means there are extra unmeasured anions in the blood, which can happen in metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. The result should be interpreted with the patient’s presentation, bicarbonate level, and overall clinical context.
Can low albumin affect the anion gap result?
Yes. Hypoalbuminemia can lower the measured anion gap because albumin is a major unmeasured anion. In that situation, a corrected anion gap may be more informative than the raw value. If albumin is low, the calculator result may underestimate the true acid-base abnormality.
How accurate is an Anion Gap Calculator?
The calculator is usually precise for the numbers entered, but the final meaning depends on the quality of the lab results and the way the formula is set up. Lab error, lab variability, and missing albumin information can affect the result. So while it is a useful screening tool and diagnostic aid, it should always be paired with clinical judgment and, when needed, additional testing such as an arterial blood gas.
If you are using the calculator and the result seems surprising, review the input values, confirm the chloride values and bicarbonate values, and consider whether a corrected value is needed before making a conclusion about the patient’s acid-base balance.