What Is the Anion Gap?
The anion gap is a calculated value that helps clinicians assess the balance of serum electrolytes in the blood. It is frequently used as a fast indicator in acid-base disorder evaluation, especially when a person may have metabolic acidosis. Rather than being measured directly, the anion gap is obtained from routine lab values on a serum chemistry panel or similar blood test.
In basic terms, the anion gap contrasts the main positively charged ions and negatively charged ions reported in a metabolic panel. The result helps identify whether there are extra unmeasured anions in the blood. That is why it can function as a useful diagnostic marker during acidosis evaluation.
The test is most often interpreted alongside the patient’s symptoms and other lab findings. A single number seldom explains the whole story, but it can powerfully point to an electrolyte imbalance or point toward a specific cause of abnormal blood chemistry.
Anion Gap Formula and Computation
The standard anion gap formula relies on the measured levels of sodium, chloride, and bicarbonate. In its most common form,:
Anion gap = Sodium − (Chloride + Bicarbonate)
This calculation uses the sodium level as the main measured cation and the chloride level plus bicarbonate level as the main measured anions. Since several charged particles are not directly included in routine testing, the formula calculates the difference between measured positive and negative charges.
A helpful way to think about the result is that the anion gap represents the space left over after measured ions are accounted for. That leftover amount indicates anion deficit or, more accurately, the presence of unmeasured anions in the blood.
Example setup:
- Sodium: 140 Chloride: 102 Bicarbonate: 24
Anion gap = 140 − (102 + 24) = 14
That number is then checked against the appropriate reference interval or lab reference range.
Reading Lab Results Before You Calculate
Before you use an anion gap calculator or calculate it manually, it is important to identify which lab panel you are reviewing. The values are usually found on a basic metabolic panel or a comprehensive metabolic panel. Each is a standard forms of blood chemistry testing, and each may contain the electrolytes needed to calculate the anion gap.
A basic metabolic panel typically includes sodium, chloride, bicarbonate, and kidney-related markers. A comprehensive metabolic panel includes those electrolytes plus additional measures that can help with broader clinical interpretation. Both panels can aid a medical interpretation of the result, but the exact report layout can vary by lab.
When reviewing the numbers, pay attention to:
- The reported sodium, chloride, and bicarbonate values Whether the lab labels bicarbonate as CO2 or total CO2 The listed lab reference range for the anion gap Any information regarding specimen quality, hemolysis, or testing limits
Since labs may use different measurement methods, one lab’s reference interval may not match another’s. Be sure to interpret the number using the range printed with the report rather than assuming a universal cutoff.
Using an Anion Gap Calculator
An anion gap calculator is a lab result calculator that runs the formula on its own once you provide the needed values. It is helpful when you want a efficient way to calculate serum anion gap from lab results without doing the arithmetic manually.
To use the calculator, input the following input values:
- Sodium Chloride Bicarbonate
After you submit those numbers, the tool returns the calculated result. That result should then be reviewed with the lab’s normal anion gap range and assessed in context.
A calculator does not replace clinical interpretation. It simply streamlines the math so you can concentrate on what the result may mean in the setting of the patient’s symptoms, the rest of the blood chemistry, and the broader question of whether there is an acid-base disorder.
Good calculator use includes:
- Entering values exactly as reported Selecting the correct units Confirming whether bicarbonate is reported directly or as total CO2 Assessing whether albumin correction is needed
What Is a Normal Anion Gap?
The normal range for the anion gap varies by the laboratory method, the analyzer, and the lab’s chosen reporting style. This is why the number must be compared with the local lab reference range rather than one standard cutoff. Various laboratories can report varied values.
In general, an in-range result is considered a normal anion gap. A result above the range suggests a high anion gap, while a result below the range suggests a low anion gap. The clinical picture matters when assessing the result.
Albumin is one of the most important reasons the “normal” range can shift. Because albumin carries negative charge, lower levels can reduce the measured gap even when another problem is present. This is why lab variation and protein status both matter when reviewing the result. Low albumin can make the gap appear lower.
Rather than focusing only on whether the number is slightly above or below a published textbook value, look at the lab’s own reference interval, the patient’s serum electrolytes, and whether the test was ordered as part of a broader metabolic panel. A full review helps place the result in context.
Elevated Anion Gap vs Decreased Anion Gap
A elevated anion gap means there are an excess of unmeasured acidic substances or negatively charged particles in the blood than expected. This pattern often points to acid buildup, especially when the bicarbonate level https://anion-gap-guide106.zenbloomer.com/posts/how-to-use-an-anion-gap-calculator-with-serum-sodium is low. A reduced anion gap is less common and may reflect low albumin, excess positively charged proteins, or a measurement issue.
These results should always be interpreted with the overall clinical context. The same number can have a different meaning depending on hydration status, kidney function, medication use, and other lab findings.
Typical Causes of a Elevated Anion Gap
Common causes of a increased anion gap include lactic acidosis, ketone-related acidosis, and renal failure. These conditions can increase the amount of unmeasured acid in the blood, leading to a larger gap.
Lactic acidosis can occur when tissues are not getting enough oxygen or when lactate production rises sharply. Ketoacidosis may develop in uncontrolled diabetes, prolonged fasting, or heavy alcohol use. Impaired kidney function can reduce the body’s ability to clear acids, allowing them to accumulate.
When a high result appears, clinicians often evaluate the patient for metabolic acidosis and related causes. The anion gap does not name the diagnosis by itself, but it helps narrow the possibilities.
Typical Causes of a Decreased Anion Gap
Frequent causes of a reduced anion gap include reduced albumin, plasma cell cancer, and laboratory error. Low albumin removes a major unmeasured negative charge from the calculation, which can push the number down.
Hypoalbuminemia is one of the most frequent explanations, especially in illness, malnutrition, or inflammation. In multiple myeloma, abnormal proteins can affect the charge balance and alter the apparent gap. A lab error or specimen problem should also be considered, particularly if the result does not fit the clinical picture.
A low value is often a signal to recheck the numbers, review the full blood chemistry, and look for albumin-related changes before drawing conclusions.
Why Albumin Correction Matters
Albumin adjustment is essential because albumin contributes significantly to the body’s negative charge. When serum albumin is low, the measured anion gap may seem falsely normal or low even if there are excess acids present. In that situation, an albumin-corrected anion gap provides a better estimate of the true acid-base status.
The correction formula adjusts the result upward when serum albumin is below normal. The exact formula may vary by institution, but a common approach adds a set amount for every 1 g/dL decrease in albumin below the usual level. Because formulas differ, use the one advised by your lab or healthcare team.
Correcting for albumin can reveal a hidden high anion gap that would otherwise be missed. This is especially useful in patients with chronic illness, fluid overload, liver disease, or any condition that lowers albumin. In other words, the corrected anion gap may be a more precise diagnostic marker for acidosis evaluation than the uncorrected number alone.
Samples of Anion Gap Calculations
Here are a handful of example lab values and a sample walkthrough to show a step-by-step calculation.
Example 1:
- Sodium: 138 Chloride: 100 Bicarbonate: 24
Stepwise calculation:
138 − (100 + 24) = 138 − 124 = 14
This result should then be compared with the lab’s standard anion gap or normal range.
Example 2:
- Sodium: 140 Chloride: 110 Bicarbonate: 18
Step-by-step calculation:
140 − (110 + 18) = 140 − 128 = 12
Even if this is within a local range, the low bicarbonate may still suggest an acid-base disorder. That is why, the anion gap should be reviewed with the rest of the metabolic profile.
Example 3 with albumin consideration:
- Sodium: 137 Chloride: 102 Bicarbonate: 20 Albumin: low
Calculation steps:
137 − (102 + 20) = 15
When serum albumin is low, the correction for albumin may increase the result and reveal a more clinically useful elevated anion gap. This is a key reason an Anion Gap Calculator that includes albumin can be especially helpful for accurate clinical interpretation.
When to Get Medical Interpretation
The anion gap is a useful tool, but it is not meant to be interpreted by itself. If the result is abnormal, or if symptoms suggest serious illness, a clinician should review it in the full overall context. That is especially true when the issue may involve acidosis, kidney dysfunction, toxic exposures, or other urgent conditions.
Get professional professional review when the result is paired with symptoms such as shortness of breath, confusion, severe vomiting, dehydration, or signs of infection. The number should also be reviewed when there is an unexpected change in electrolyte levels, worsening kidney function, or a suspected acid-base imbalance.
In practice, the anion gap is one piece of the larger clinical picture. Clinicians look at the basic metabolic panel, the comprehensive metabolic panel, albumin, kidney markers, and the patient’s history to determine how to interpret the value and whether further testing is needed.
FAQ
How do you calculate serum anion gap from lab results?
Use the anion gap formula: sodium minus the sum of chloride and bicarbonate. In other words, anion gap = sodium − (chloride + bicarbonate). This lets you calculate serum anion gap from lab results on a chemistry panel.
What lab values do I need for an anion gap calculator?
You need sodium, chloride, and bicarbonate. These values are usually found on a basic metabolic panel or comprehensive metabolic panel. Some calculators also allow albumin correction if serum albumin is available.
What is a normal anion gap range?
The normal anion gap depends on the lab’s reference interval or lab reference range. Because there is lab variation, always compare the result with the range listed on the report rather than relying on one universal number. Various labs may report different reference values. Be sure to check the printed report for the specific interval.
Why is albumin used to correct the anion gap?
Albumin is a major negatively charged protein in blood. If serum albumin is low, the measured gap can look lower than it really is. Albumin correction helps estimate the corrected anion gap more accurately when albumin is abnormal. This adjustment can reduce misinterpretation when the protein level is low.
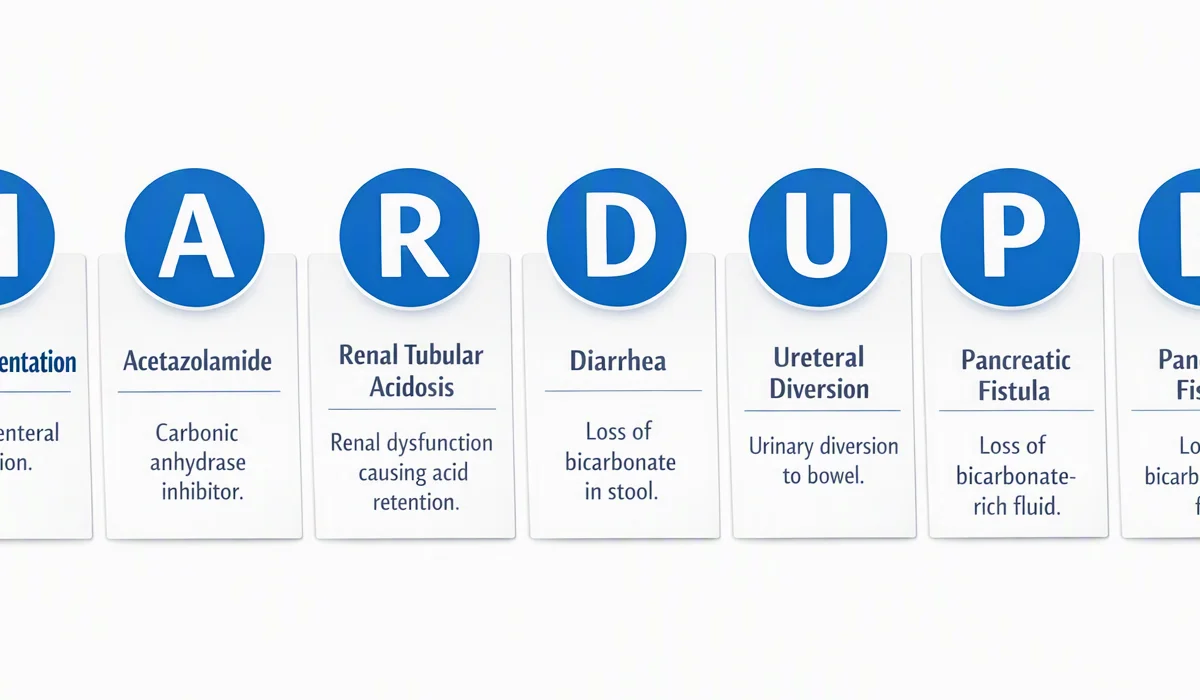
What does a high or low anion gap mean?
A high anion gap often suggests extra unmeasured acids and may be seen with lactic acidosis, ketoacidosis, or renal failure. A low anion gap may point to hypoalbuminemia, multiple myeloma, or lab error. The meaning depends on the overall clinical context and should be reviewed by a healthcare provider. In combination, these findings can suggest an underlying issue.