If you want to work out anion gap values accurately, the key is knowing how the anion gap is built from routine electrolytes and why low albumin can mask a clinically important abnormality. An Anion Gap Calculator can speed up the math, but the real benefit comes from knowing how to interpret the result in acid-base analysis.
Defining the Anion Gap?
The anion gap is a derived number that helps measure the difference between measured positive and negative charges in the blood. It is usually obtained from common lab values on a blood test, especially sodium, chloride, and bicarbonate. In many cases, potassium may also be added depending on the formula being used.
Clinically, the anion gap is a valuable diagnostic aid in evaluating an acid-base disorder. It helps identify whether an unexplained metabolic acidosis may be present and whether the cause is likely to be due to unmeasured acids, changes in proteins, or shifts in serum electrolytes. The calculation is part of a larger metabolic panel or basic metabolic panel, which provides a picture of key lab values.
The concept is straightforward: blood contains positively charged ions and negatively charged ions. The measured ions do not cover everything present, so the “gap” indicates unmeasured components. A normal result falls within a reference range that varies slightly by laboratory and by whether potassium is included in the formula.
How exactly the Anion Gap Calculator Functions
An anion gap calculator is designed to streamline the gap calculation using the lab values entered from a basic metabolic panel or similar electrolyte test. Typically, the calculator uses sodium, chloride, and serum bicarbonate. Certain versions also accept potassium, which slightly alters the formula.
At its core, the calculator applies an anion gap formula such as:
Anion gap = Sodium − (Chloride + Bicarbonate)
If potassium is included, the formula changes to:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
This computerized measurement can help reduce math errors and make interpretation faster when reviewing serum electrolytes. The calculator may also help highlight values that are outside the normal range, which is especially helpful when assessing possible electrolyte imbalance or an acid-base disorder.
However, the calculator is only as useful as the data provided. A missing or inaccurate lab value can lead to misleading interpretation. That is why the clinical significance of the number depends on the full lab context, especially the bicarbonate level, the patient’s albumin status, and any evidence of acid-base disturbance.

Adjusted Anion Gap: Definition and Formula
The corrected anion gap is the anion gap corrected for the effect of albumin, which is the chief anion-bearing protein in blood. Because albumin has a strong effect on the normal anion gap, a low albumin level can make the gap appear artificially normal. That is where albumin correction becomes important.
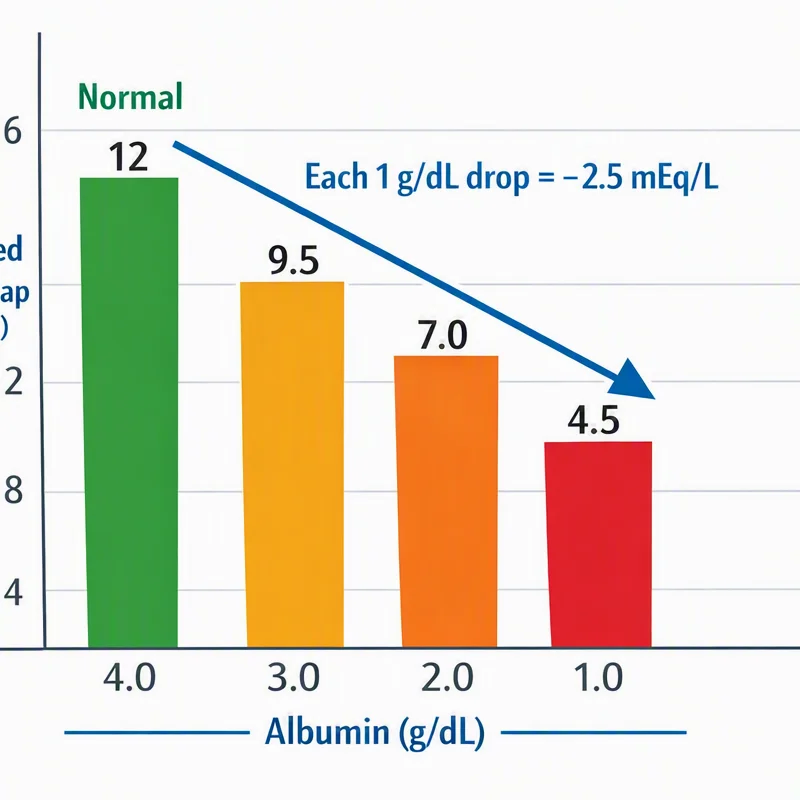
The purpose of this correction is to better reflect true acid-base balance. In a patient with hypoalbuminemia, the measured gap may overlook the presence of unmeasured acids. The adjusted value is sometimes called the corrected anion gap.
A common correction formula is:
Corrected anion gap = Measured anion gap + 2.5 × (4.0 − serum albumin in g/dL)
This is an correction coefficient for albumin used to estimate how much the low albumin is lowering the result. Different references may use slightly different factors, but the goal is the same: adjust for albumin so the interpretation is more accurate.
Why does this matter? Albumin is one of the major anion-carrying proteins in plasma. When it drops, the body may preserve electroneutrality by increasing chloride or bicarbonate-related shifts, and the anion gap can look deceptively normal. Using the effective value improves clinical interpretation in acid-base analysis.
Step-by-Step Guide: How to Calculate Effective Anion Gap
To work out the effective anion gap, follow a straightforward stepwise approach using the available lab values. This remains the practical method clinicians use when reviewing serum electrolytes and deciding whether the patient has a hidden high-gap disorder.
Step 1: Review the lab values from the blood test.
- Sodium Chloride Bicarbonate Serum albumin
Step 2: Calculate the measured anion gap using the standard formula.
Anion gap = Sodium − (Chloride + Bicarbonate)
Step 3: Contrast the result with the laboratory reference range.
Step 4: If albumin is low, follow the calculation formula for albumin adjustment.
Corrected anion gap = Measured anion gap + 2.5 × (4.0 − serum albumin)
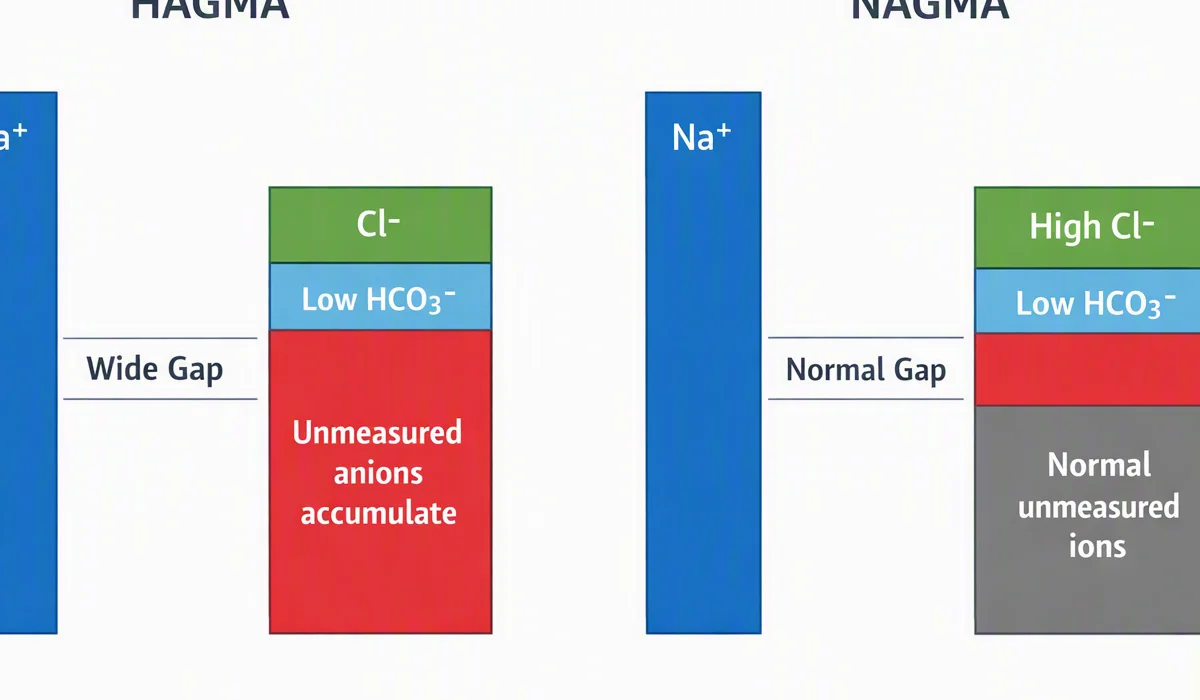
Step 5: Interpret the corrected anion gap in the context of the patient’s acid-base state.
This is a worked example. Suppose the labs show:
- Sodium: 140 Chloride: 104 Bicarbonate: 18 Serum albumin: 2.0 g/dL
Measured anion gap:
140 − (104 + 18) = 18
Albumin correction:
Corrected anion gap = 18 + 2.5 × (4.0 − 2.0)
Corrected anion gap = 18 + 5 = 23
In this case, the measured result is elevated, and the albumin-adjusted value is even higher. This suggests a more significant underlying problem than the raw number alone would show.
When using an Anion Gap Calculator, be sure to check whether the tool includes albumin correction. Some calculators provide only the standard result, while others display both the measured and corrected values. In clinical practice, the adjusted result can be especially helpful when the serum albumin is low.
Why Albumin Changes the Anion Gap
Hypoalbuminemia affects the anion gap because albumin has a minus charge and functions as a major unmeasured anion in plasma. When albumin falls, the body’s charge balance shifts, often reducing the observed anion gap even if a true acid-base problem exists.
This explains why albumin matters so much in acid-base balance. In people with low albumin, a normal anion gap may not actually rule out a high-gap process. Without adjustment, the lab pattern can look less abnormal than it truly is.
Several physiologic factors help explain this effect:
- Albumin is a major source of unmeasured negative charge. Shifts in protein binding can alter the distribution of ions. The body may compensate by shifting chloride or bicarbonate.
Because of this, clinicians often rely on albumin correction when the clinical picture suggests an acid-base disorder but the basic calculation seems borderline. In that setting, https://anion-gap-reference112.timeforchangecounselling.com/calculating-anion-gap-with-units the corrected number gives a better estimate of the true gap.
How to Interpret the Result
Understanding the anion gap is not just about judging whether the number is high or normal. It is about linking the measurement to the overall acid-base picture. A high anion gap often indicates the presence of unmeasured acids and can be seen in metabolic acidosis.
Common high-gap processes include lactic acidosis and ketoacidosis. In both situations, acid accumulates and bicarbonate is consumed, which elevates the gap. If the corrected value is elevated, the finding becomes even more important because low albumin may have masked the severity of the problem.
Alternatively, a normal result does not always mean the problem is resolved. A normal anion gap can still occur in metabolic acidosis, particularly when bicarbonate falls and chloride rises in a way that preserves the calculated difference. This is why the result should be interpreted alongside pH, bicarbonate, and the rest of the clinical assessment.
Useful interpretation tips:
- A high corrected gap supports a high-gap metabolic acidosis. A normal measured gap with low albumin may still hide an elevated corrected gap. Trend changes can be more informative than a single value. Always compare the result with the patient’s symptoms and other lab values.
The main goal of gap calculation is to aid thoughtful clinical interpretation, not to replace it. The number is a tool for spotting patterns in serum electrolytes and for identifying whether extra workup is needed.
Common Causes of a High or Low Anion Gap
Many conditions can shift the gap higher or down. A increased anion gap often suggests too much acid, while a low result may reflect a shift in proteins, lab methods, or unusually high chloride. Knowing the cause helps connect the number to the patient’s overall status.
Common causes of a high anion gap include:
- Lactic acidosis, due to tissue hypoperfusion, sepsis, or other causes of impaired oxygen delivery Ketoacidosis, including diabetic ketoacidosis, starvation ketoacidosis, or alcohol-related ketosis Renal failure, where acid excretion is reduced and unmeasured acids accumulate Toxic alcohols, such as methanol or ethylene glycol, which can generate acid metabolites
Common causes of a low or apparently normal gap include:
- Hyperchloremia, which can offset bicarbonate loss and keep the calculation from rising Significant hypoalbuminemia, which lowers the measured value Lab variation or measurement issues that affect sodium, chloride, or bicarbonate Higher unmeasured cations in certain uncommon settings
Some disorders, such as renal failure, may also produce mixed patterns depending on the stage and the patient’s fluid status. Likewise, toxic alcohols often need prompt recognition because the gap may rise before other symptoms become obvious.
Another important cause of an unusual low or altered result is multiple myeloma. This condition can affect protein composition in the blood and change how the calculation behaves, which is one reason albumin and total protein context matter.
When the pattern seems inconsistent, revisit the basic metabolic panel, the albumin level, and the correction formula. A close review of lab values often reveals why a seemingly simple blood test produces a complex result.
FAQ
What formula is used to calculate the anion gap?
The most common anion gap equation is sodium minus the sum of chloride and bicarbonate: sodium − (chloride + bicarbonate). Some formulas also add potassium, but many routine calculations use the simpler form from a basic electrolyte panel. The precise calculation depends on the lab and the clinical interpretation being used.
How do you adjust the anion gap for albumin?
Start with calculating the observed anion gap from the electrolyte panel. After that, use the albumin correction factor: corrected anion gap = measured anion gap + 2.5 × (4.0 − serum albumin). This adjustment helps account for albumin so low albumin does not mask a true gap abnormality.
Why is albumin used to correct the anion gap?
Albumin is a major negatively charged protein in blood, so changes in albumin affect the gap calculation. In reduced albumin, the measured gap may look falsely low or normal. Correcting for albumin improves the accuracy of acid-base evaluation and the overall assessment of acid-base equilibrium.
What is the significance of a high anion gap?
A increased anion gap usually suggests the presence of unmeasured acids and is commonly associated with metabolic acid buildup. Important causes include elevated lactic acid, ketone accumulation, renal failure, and toxic ingestions. The result should always be interpreted alongside symptoms and other lab values.
Can the anion gap be normal even when metabolic acidosis is present?
Yes. A normal anion gap can occur even with metabolic acidosis, especially when bicarbonate falls and chloride rises in a way that preserves the calculation. This is one reason the result should be reviewed in the context of the entire metabolic panel, serum albumin, and the overall clinical picture.
In real-world use, an Anion Gap Calculator is especially useful when it supports a stepwise assessment of the blood test: review the electrolytes, calculate the raw gap, calculate anion gap using the standard formula, then corrected anion gap values when albumin is low. That approach offers a clearer picture of whether the patient has a genuine acid-base disorder or a result that requires further investigation.