What Does Mean the Anion Gap?
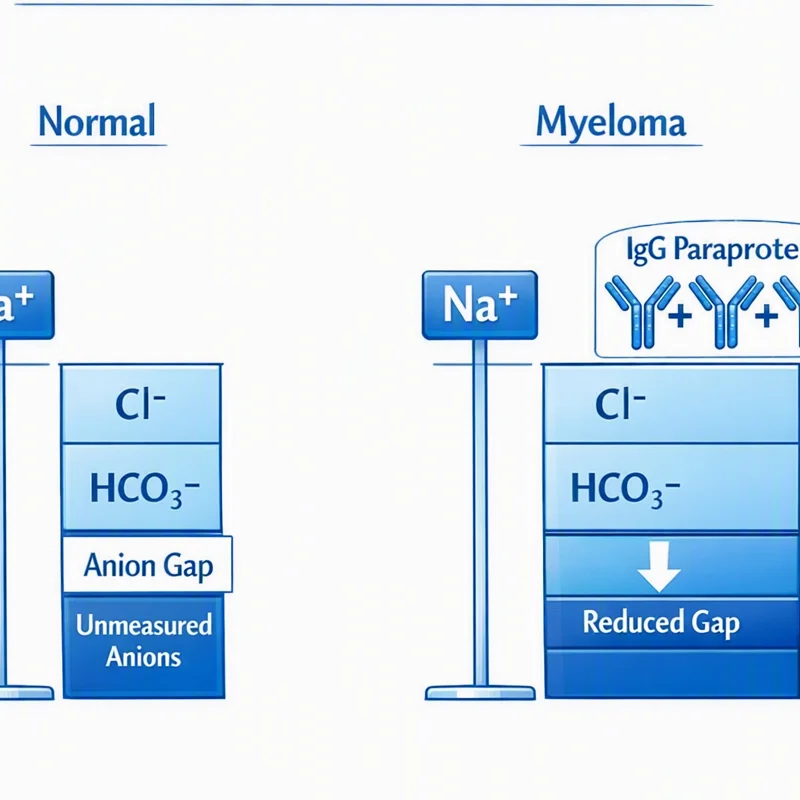
The anion gap serves as a derived value that assists clinicians evaluate acid-base balance by comparing the major measured cations and anions in the blood. It is usually calculated from routine serum electrolytes, especially sodium, chloride, and bicarbonate. As the body maintains electrical neutrality, the anion gap measures the difference between measured positively charged and negatively charged particles, indirectly indicating unmeasured ions.
In clinical practice, the anion gap is especially useful when evaluating metabolic acidosis. A shift in the gap often points toward excess acids, lost bicarbonate, or laboratory patterns that require a broader diagnostic approach. Because it relies on common laboratory values, it is one of the simplest tools for identifying an acid-base disorder and narrowing the differential diagnosis.
While the exact number can vary based on the lab’s reference range, a normal result usually suggests that measured cations and anions are in expected balance. A higher-than-expected result can indicate high anion gap acidosis, while a normal value in the setting of acidosis may indicate normal anion gap or hyperchloremic processes. That distinction is central to https://anion-gap-test178.capitaljays.com/posts/could-hypoxia-raise-the-anion-gap clinical interpretation.
How the Anion Gap Calculator Works
An anion gap calculator simplifies the anion gap formula so that clinicians can promptly interpret laboratory values and assess for an electrolyte imbalance. The traditional formula is:
Anion gap = sodium − (chloride + bicarbonate)
Some versions add potassium, but most bedside interpretation relies on the simplified formula above. The calculator uses serum sodium, serum chloride, and serum bicarbonate to estimate the amount of unmeasured anions in the plasma. A higher gap usually suggests accumulation of organic acids or other unmeasured substances.
The calculator becomes even more helpful when albumin is abnormal. Because albumin is a negatively charged protein and a major unmeasured anion, low albumin can make the gap appear falsely normal. That is why many clinicians apply albumin correction before final interpretation. The output is often a corrected anion gap, which gives a better picture of the patient’s underlying acid-base status.
In real-world use, the calculator supports rapid blood gas analysis and complements the exam of acid-base patterns. It does not replace clinical judgment, but it helps with the first step in recognizing metabolic acidosis, especially when the cause is not immediately obvious.
Why the Anion Gap Matters in Acid-Base Balance
The anion gap matters because it helps distinguish different categories of acid-base balance disorders. When metabolic acidosis is present, the gap can indicate either a high anion gap or a normal anion gap pattern. This separation is significant because the causes, urgency, and treatment strategies are often different.
In high gap acidosis, the body has collected unmeasured acids. In normal gap acidosis, bicarbonate is often lost and replaced by chloride, which keeps the gap but still results in acidemia. This is why the anion gap is not just a number; it is a lens for understanding the underlying buffering system and how the body reacts to an acid-base disorder.
It also can reveal a mixed disorder. For example, a patient may have a metabolic acidosis and a second process affecting pH, such as respiratory compensation that is not enough or exaggerated. In these cases, the anion gap adds structure to the clinical interpretation of the patient’s labs and symptoms.
Because the gap is tied to measured and unmeasured ions, it is a useful link between routine chemistry testing and deeper physiologic reasoning. That makes it a key tool in both routine medicine and urgent evaluation.
How to Read a High Anion Gap
A high anion gap usually means that unmeasured acids are present in excess. This is a typical finding in many serious causes of metabolic acidosis, and it should lead to a careful search for the source of the acid load.
Typical causes include lactic acidosis, ketoacidosis, renal failure, and toxic ingestions. In lactic acidosis, tissue reduced blood flow, sepsis, seizures, or severe physiologic stress can raise lactate production. In ketoacidosis, ketone bodies accumulate when insulin is lacking or when starvation and alcohol-related states change metabolism. Renal failure can limit acid excretion, allowing unmeasured acids to build up. Toxic alcohol ingestion is another important cause because substances such as methanol or ethylene glycol generate acid metabolites that increase the gap.
When the gap is elevated, the next question is not just “Is it high?” but “Why is it high?” That requires combining the anion gap with the patient’s history, exam, and other lab data. A patient with acidemia, elevated lactate, and hypotension may have lactic acidosis. Someone with hyperglycemia or starvation may suggest ketoacidosis. Kidney function tests, osmolar calculations, and toxicology clues may be needed in other scenarios.
A high gap is especially important because it can signal a urgent condition that needs rapid treatment. The anion gap calculator helps spot the pattern early, but the clinician must then relate it to the patient’s overall presentation.
How to Interpret a Normal Anion Gap
A normal gap does not exclude metabolic acidemia. Instead, it typically indicates loss of bicarbonate with a compensatory rise in chloride, causing hyperchloremic acidosis. This is also referred to as non-gap acidosis.
One of the most common causes is loose stools, where the body excretes bicarbonate-rich intestinal fluid. A further important cause is tubular kidney acidosis, in which the kidneys do not process acid or bicarbonate normally. In either case, the drop in bicarbonate is central, but the anion gap remains in the expected range because chloride rises to preserve electroneutrality.
This picture can be easy to miss if attention is placed only on the pH. A patient may be acidemic with low bicarbonate but still have a normal gap. That is why, a full review of blood electrolytes matters. The blood chloride level often rises relative to bicarbonate, forming the lab pattern that supports a normal-gap process.
Normal-gap patterns are also helpful when evaluating treatment effects. For example, after a high-gap acidosis begins to resolve, the gap may normalize while bicarbonate remains low, or the patient may develop a mixed picture. Careful tracking prevents misclassification and supports better medical interpretation.
Albumin level Adjustment and Other Key Adjustments
Albumin is among the most important elements to evaluate when interpreting the anion gap. Since albumin makes up a large part to the pool of unmeasured anions, hypoalbuminemia can lower the measured gap and obscure a clinically significant acidosis. In these cases, albumin correction is crucial.
The resulting corrected anion gap better reflects the true acid burden. Without this adjustment, a patient may seem to have a normal gap even when a high-gap process is present. This is especially important in ill patients with inflammation, malnutrition, liver disease, or critical illness, where low serum albumin is often seen.
Albumin’s role is tied to protein binding and the overall charge balance in plasma. When albumin falls, the baseline anion gap falls too. That means the lab result has to be interpreted in context rather than as an isolated number. A clinician using an anion gap calculator should therefore check whether the tool includes an albumin adjustment or whether correction must be done separately.
Other adjustments may also matter depending on the setting, but albumin is the major one in routine practice. It is a reminder that not all “normal” results are truly normal. If the patient has hypoalbuminemia, a corrected value may reveal hidden high gap acidosis that changes the differential diagnosis and treatment priorities.
Stepwise: How to Evaluate Acid-Base Equilibrium
A practical approach begins with the full set of available data: serum electrolytes, an arterial blood gas, and the clinical context. The purpose is to establish whether there is acidemia or alkalemia, whether the problem is metabolic or respiratory, and whether the anion gap helps explain the pattern.
Initially, review the pH on the blood gas. If the pH is low, acidemia is present. Then, examine bicarbonate and carbon dioxide to decide whether the primary problem is metabolic or respiratory. If bicarbonate is low, metabolic acidosis is likely. At that point, calculate or review the anion gap using sodium, chloride, and bicarbonate.
Next, assess whether respiratory compensation is appropriate. The lungs often reduce carbon dioxide in response to metabolic acidosis. If compensation is not as expected, another process may be present. This is where blood gas analysis and the electrolyte panel should be interpreted together rather than separately.
After that, decide whether the pattern is high-gap or normal-gap. A high-gap pattern should trigger evaluation for lactic acidosis, ketoacidosis, renal failure, or toxic alcohol exposure. A normal-gap pattern should raise suspicion for diarrhea, renal tubular acidosis, or other sources of bicarbonate loss.
Lastly, review whether albumin is low and whether a corrected anion gap is needed. This step improves accuracy and can reveal a mixed disorder that would otherwise be overlooked. In short, the process is: assess pH, identify the primary disorder, calculate the gap, correct for albumin, and then interpret the result in context.
Typical Pitfalls in Anion Gap Analysis
One of the main mistakes is failing to notice lab error or specimen issues. A single abnormal value should always be verified against the other values of the panel and the clinical picture. If the numbers do not make physiologic sense, repeat testing may be necessary before drawing conclusions.
A common error is ignoring the reference range used by the laboratory. Different analyzers and institutions may have somewhat different normal ranges, so the same numeric result can be interpreted in another way depending on the setting. This is why the anion gap should never be treated as a isolated diagnosis.
It can also be easy to miss a mixed acid-base disorder. For example, a patient may have a high anion gap and a coexisting metabolic alkalosis, or a normal gap with a respiratory process layered on top. The delta gap is useful here because it compares the change in the anion gap to the change in bicarbonate and can help show whether additional processes are present.
A further mistake is forgetting that low albumin changes the baseline. If hypoalbuminemia is present, the measured anion gap may underestimate the severity of the disturbance. Careful albumin correction lowers this risk and improves diagnostic reliability.
Situations for Using an Anion Gap Calculator
An anion gap calculator is particularly useful when a prompt, accurate evaluation is needed for clinical decision making. It is especially valuable during emergency evaluation when a patient presents with vomiting, altered mental status, shock, dyspnea, or signs of acidemia. In these situations, rapid recognition of an acid-base disorder can affect immediate care.
The calculator is also important in critical care, where serial labs are reviewed repeatedly and subtle changes can matter. Patients with sepsis, kidney dysfunction, diabetes, intoxication, or gastrointestinal losses often have variable electrolyte patterns. A calculator helps structure those values into a usable interpretation.
In everyday clinical use, the tool facilitates a more structured approach to any suspected acid-base disorder. It can help distinguish metabolic acidosis from other problems, identify when albumin correction is needed, and direct next-step testing. Because it links electrolytes, albumin, and the broader clinical picture, it is beyond a math aid; it is part of the diagnostic workflow.
For best results, use it alongside the patient’s symptoms, medications, kidney function, glucose, lactate, ketones, and blood gas results. That broader context turns a number into actionable information.
Frequently Asked Questions About Anion Gap and Acid-Base Balance
What is the anion gap and why is it important?
The anion gap is a derived value from sodium, chloride, and bicarbonate that helps measure acid-base balance. It is important because it helps spot metabolic acidosis and distinguish between high anion gap and normal anion gap patterns, which have varying causes and treatment priorities.
How do you calculate the anion gap from lab values?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate: sodium − (chloride + bicarbonate). An Anion Gap Calculator performs this calculation for you using serum electrolytes. If albumin is low, albumin correction may be needed for a better adjusted result.
What does a high anion gap mean in acid-base balance?
A high anion gap usually means there are extra unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohol ingestion. It often signals a medically significant form of metabolic acidosis that needs prompt evaluation.
How does low albumin affect the anion gap?
Hypoalbuminemia decreases the measured anion gap because albumin is a major unmeasured anion. That can cause a true high-gap process appear normal. Using a corrected anion gap helps adjust for this effect and supports clinical interpretation.
Can a normal anion gap still occur with metabolic acidosis?
Yes. A normal anion gap can still be seen with metabolic acidosis, especially when there is bicarbonate loss replaced by chloride. Common causes include diarrhea and renal tubular acidosis, often described as hyperchloremic acidosis or normal gap acidosis.